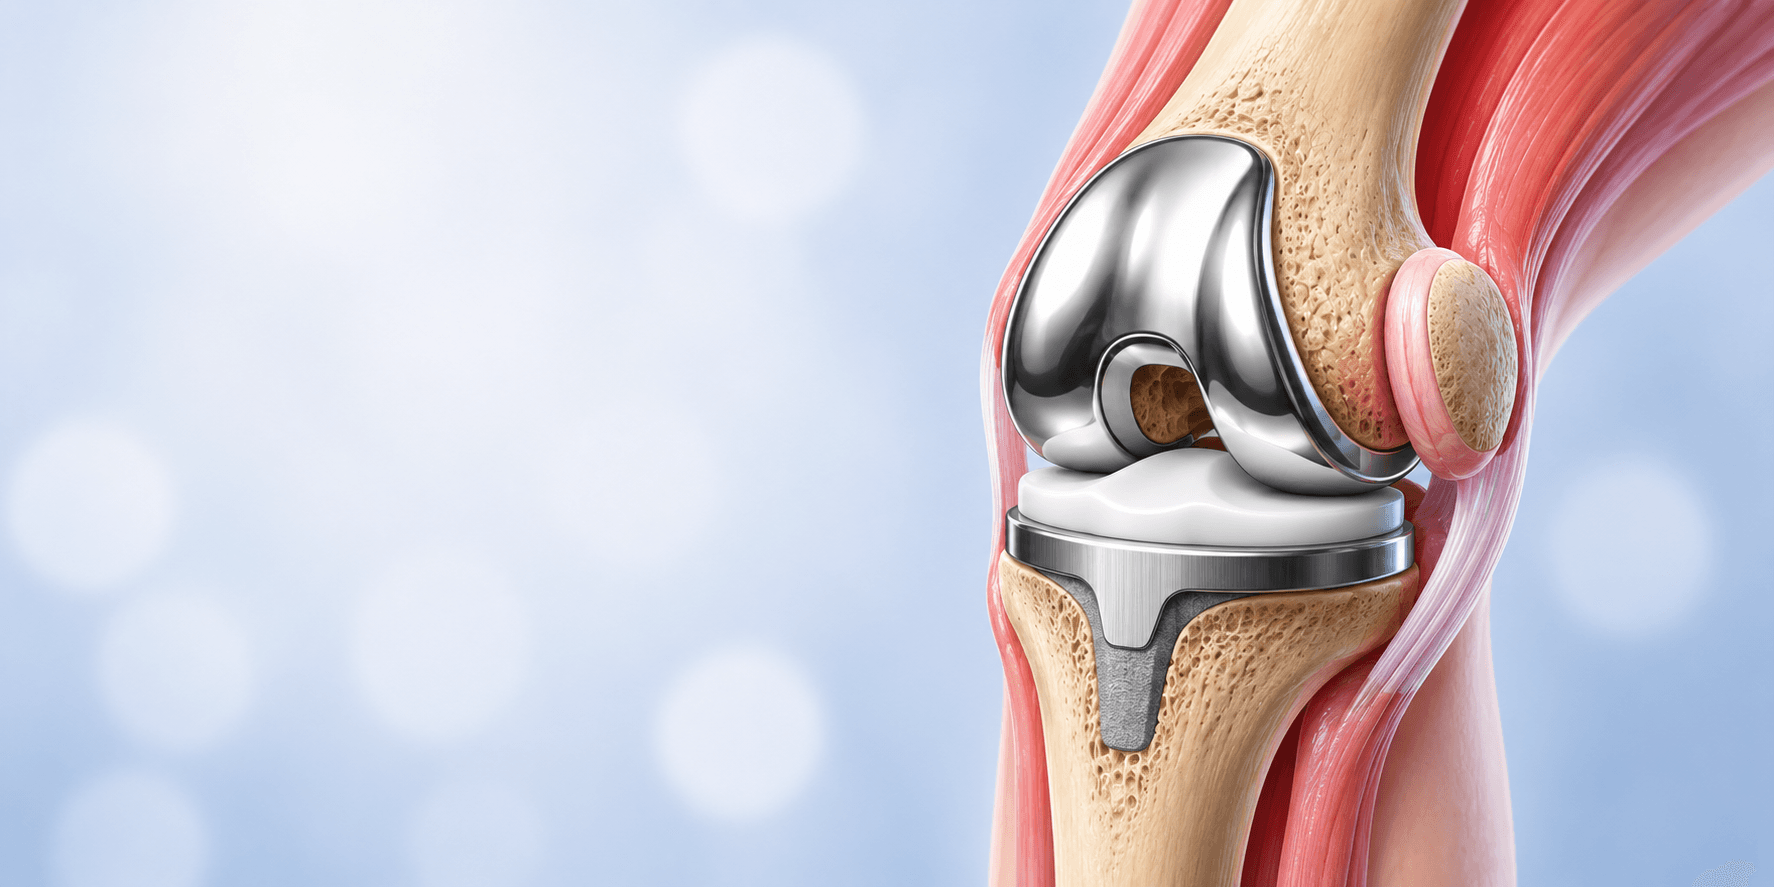
Knee replacement surgery, also called knee arthroplasty, is an operation in which damaged surfaces of the knee joint are replaced with artificial components. The goal is not simply to replace an X-ray abnormality—it is to reduce pain, improve function and help the patient return to a more active and independent life.
The most common reason for knee replacement is advanced osteoarthritis, but surgery may also be considered for certain patients with rheumatoid arthritis, post-traumatic arthritis, severe joint damage or other conditions causing persistent pain and loss of function.
Knee replacement is a major operation, but modern surgical techniques, anesthesia, pain management and early rehabilitation have made recovery faster and more predictable for many patients.
This guide explains the complete patient journey—from the decision to operate through surgery, anesthesia, hospital recovery, discharge and long-term rehabilitation.
What Is Knee Replacement Surgery?
The knee is a joint formed mainly by the lower end of the thigh bone (femur), the upper end of the shin bone (tibia) and the kneecap (patella). Healthy cartilage allows these surfaces to move smoothly.
When the cartilage becomes severely damaged, the bones can rub against each other. This can cause pain, stiffness, swelling, deformity and difficulty walking.
During knee replacement, the damaged joint surfaces are carefully prepared and replaced with artificial components designed to restore a stable, functional joint.
Why Do People Need Knee Replacement?
Knee replacement is usually considered when knee pain and loss of function have become significant and non-surgical treatments no longer provide adequate relief.
- Severe osteoarthritis.
- Rheumatoid or inflammatory arthritis.
- Post-traumatic arthritis after a previous knee injury.
- Severe cartilage or joint damage.
- Progressive knee deformity.
- Persistent pain that interferes with daily activities.
- Difficulty walking, climbing stairs or standing.
- Night pain or rest pain.
- Significant stiffness and reduced knee movement.
- Failure of appropriate non-surgical treatment.
When Is Knee Replacement Actually Needed?
There is no single X-ray finding or age that automatically means a patient needs knee replacement. The decision should be based on the combination of symptoms, physical examination, imaging and the effect of the knee problem on quality of life.
- Pain is persistent or severe.
- Pain limits walking or everyday activities.
- Sleep is affected.
- The knee has significant stiffness or deformity.
- Conservative treatments have been tried appropriately.
- The expected benefits of surgery outweigh the risks.
A patient with severe X-ray arthritis but little pain may not need surgery immediately. Conversely, a patient whose symptoms severely limit daily life may be an appropriate candidate when other treatments have failed.
Do You Need Knee Replacement Before Trying Other Treatments?
Usually, knee replacement is not the first treatment for arthritis. Depending on the individual patient, doctors may first recommend exercise, physiotherapy, weight management, walking aids, medicines or injections.
- Physical therapy and strengthening.
- Activity modification.
- Weight management when appropriate.
- Pain-relieving medicines when medically suitable.
- Walking aids or braces in selected patients.
- Injections in selected circumstances.
When these measures no longer provide sufficient relief and the knee continues to significantly affect quality of life, replacement may become appropriate.
Types of Knee Replacement
1. Total Knee Replacement
Total knee replacement is the most common form of knee arthroplasty. The damaged surfaces of the femur and tibia are replaced, and the kneecap may also be resurfaced depending on the surgeon’s assessment and surgical plan.
2. Partial Knee Replacement
Partial knee replacement replaces only the damaged compartment of the knee when disease is appropriately limited and the remaining joint structures and ligaments are suitable.
3. Revision Knee Replacement
Revision surgery is performed when a previous knee replacement develops a significant problem such as infection, loosening, instability, fracture or substantial wear.
Total vs Partial Knee Replacement
Partial knee replacement is not simply a smaller version of total knee replacement. It is suitable only for carefully selected patients whose arthritis is confined to an appropriate compartment and whose knee has suitable stability and function.
- Total replacement treats more extensive joint disease.
- Partial replacement preserves more of the patient’s native knee.
- Partial replacement may allow faster recovery in appropriately selected patients.
- Not every patient with arthritis is a candidate for partial replacement.
The final choice should be made after clinical examination, imaging and assessment of the entire knee.
What Happens Before Knee Replacement Surgery?
Preparation begins before the day of surgery. The goal is to identify medical risks, optimize existing conditions and prepare the patient for rehabilitation.
- Review of medical history.
- Physical examination.
- Assessment of the knee and walking pattern.
- X-rays and other imaging when required.
- Blood tests.
- Blood pressure assessment.
- Heart assessment when indicated.
- Medication review.
- Anesthesia assessment.
- Assessment of diabetes and blood sugar control when relevant.
- Assessment of weight and nutritional status.
- Evaluation for active infection.
- Planning for postoperative support and physiotherapy.
Why Medical Conditions Should Be Optimized Before Surgery
Knee replacement is elective in most cases, which gives the medical team an opportunity to optimize health before surgery.
- Diabetes should be appropriately controlled.
- Blood pressure should be managed.
- Anemia should be identified and treated when appropriate.
- Active infections should be treated before elective surgery.
- Smoking should ideally be stopped before surgery.
- Medications that affect bleeding may need adjustment under medical supervision.
- Weight and nutritional issues should be addressed when appropriate.
Do not stop blood thinners, diabetes medicines or other prescription medicines on your own. Your surgeon and anesthetist should provide specific instructions.
Prehabilitation: Exercises Before Knee Replacement
Strengthening the muscles around the knee before surgery can help a patient enter the operation in better physical condition. This is sometimes called prehabilitation.
- Quadriceps strengthening.
- Straight-leg exercises when appropriate.
- Gentle range-of-motion exercises.
- Hip and core strengthening.
- Upper-body strengthening for walking-aid use.
- Walking or low-impact cardiovascular activity as tolerated.
The exercises should be adapted to the patient’s pain, mobility and medical condition.
What Anesthesia Is Used for Knee Replacement?
Knee replacement can be performed under spinal or regional anesthesia, general anesthesia, or a combination of techniques. The anesthetic plan is individualized after assessment by the anesthesia team.
Spinal Anesthesia
Spinal anesthesia involves injecting anesthetic medicine into the lower back to temporarily numb the lower part of the body. The patient may remain awake or receive medication to make them relaxed and sleepy.
General Anesthesia
With general anesthesia, the patient is unconscious during the operation and the anesthesia team continuously monitors breathing, circulation and other vital functions.
Nerve Blocks and Local Pain Infiltration
The anesthesia or surgical team may use nerve blocks or local anesthetic around the knee as part of a multimodal pain-control plan.
Which Anesthesia Is Better?
There is no single anesthesia technique that is best for every patient. The choice depends on overall health, medications, previous anesthesia experience, airway considerations, patient preference and the anesthetist’s assessment.
The anesthesia team will explain the planned technique and discuss its benefits, limitations and risks before surgery.
Is ICU Required After Knee Replacement?
Routine ICU admission is generally not required after an uncomplicated knee replacement. Most patients are monitored initially in a postoperative recovery area and then transferred to the orthopedic ward or appropriate postoperative unit.
An ICU or higher-dependency level of monitoring may be required if a patient has significant medical problems, an unexpected complication or a specific need for intensive monitoring.
The need for ICU care should therefore be based on the patient’s medical condition rather than the knee replacement itself.
How Long Does Knee Replacement Surgery Take?
The surgical portion of a primary knee replacement commonly takes around one to two hours, although the total time spent in the operating and recovery areas is longer.
Complex deformities, previous surgery, revision procedures and additional medical considerations can make the operation longer.
What Happens on the Day of Surgery?
- You arrive at the hospital according to the surgical team’s instructions.
- Your identity, procedure and surgical site are confirmed.
- Your medical history and medications are reviewed.
- The anesthesia team evaluates you.
- The surgical leg is confirmed and marked when appropriate.
- You receive the planned anesthesia.
- The surgical team performs the knee replacement.
- You are transferred to the recovery area after surgery.
- Your pain, blood pressure, breathing and other vital signs are monitored.
- Once stable, you are transferred to the appropriate postoperative unit.
The Knee Replacement Surgery: Step by Step
Step 1: Positioning and Sterile Preparation
The patient is positioned carefully, the leg is prepared with antiseptic solution and sterile drapes are applied.
Step 2: Surgical Incision
The surgeon makes an incision over the front of the knee and gains access to the joint through the appropriate surgical approach.
Step 3: Assessment of the Damaged Joint
The surgeon evaluates the extent of cartilage loss, deformity, ligament balance and bone condition.
Step 4: Preparation of the Femur
The damaged end of the femur is carefully cut and shaped to accept the femoral implant.
Step 5: Preparation of the Tibia
The damaged upper surface of the tibia is prepared to receive the tibial component.
Step 6: Trial Components
Temporary trial components may be inserted so the surgeon can assess alignment, stability, movement and the balance of the knee.
Step 7: Implant Placement
The final components are positioned after the surgeon is satisfied with the preparation and balance of the knee.
Step 8: Polyethylene Bearing
A durable plastic bearing is placed between the femoral and tibial components to provide a smooth articulating surface.
Step 9: Patella Assessment
The surgeon evaluates the kneecap. Depending on the patient and surgical strategy, the underside of the patella may be resurfaced with a plastic component.
Step 10: Final Testing
The knee is moved through its range of motion and assessed for stability, alignment and appropriate tracking.
Step 11: Closure
The surgical wound is closed and covered with an appropriate dressing.
What Are Knee Replacement Implants Made Of?
Modern knee replacement systems typically use a combination of metal and highly durable plastic components.
- A femoral component, commonly made from a metal alloy.
- A tibial component, commonly consisting of a metal baseplate.
- A polyethylene bearing between the femoral and tibial components.
- A patellar component when patellar resurfacing is performed.
The exact implant design and materials depend on the manufacturer, implant system, patient anatomy and surgeon’s preferred technique.
Cemented vs Cementless Knee Replacement
Knee implants may be fixed to bone using bone cement or designed for biological fixation as the bone grows onto the implant surface. Some systems use different fixation strategies for different components.
The choice depends on bone quality, age, anatomy, surgeon experience and implant system. There is no single fixation method that is ideal for every patient.
What Is Robotic Knee Replacement?
Robotic-assisted knee replacement uses computer-based planning and specialized instruments to help the surgeon execute the planned bone cuts and implant positioning.
The robot does not independently perform the operation. The surgeon remains responsible for planning, decision-making and execution.
Robotic assistance may be useful in selected cases, but it does not mean that a conventional knee replacement is inferior. The most appropriate technology depends on the patient, implant system and surgeon’s experience.
Does Robotic Knee Replacement Guarantee Better Results?
No. Robotic assistance can improve planning and precision in certain aspects of surgery, but technology alone does not guarantee better pain relief, function or long-term outcomes for every patient.
The quality of patient selection, surgical technique, implant choice, infection prevention and postoperative rehabilitation remain extremely important.
What Happens Immediately After Surgery?
- You are monitored in the postoperative recovery area.
- Pain is assessed and treated.
- Blood pressure, heart rate and oxygen levels are monitored.
- The surgical dressing is checked.
- Your leg circulation and neurological status may be assessed.
- You may receive medicines to reduce the risk of blood clots.
- You will be encouraged to begin movement when medically safe.
When Will I Start Walking After Knee Replacement?
Early mobilization is an important part of modern knee replacement recovery. Many patients are helped to stand and walk with a physiotherapist or trained healthcare professional on the day of surgery or shortly afterward, depending on their condition.
- Standing with assistance.
- Walking with a walker or crutches.
- Simple ankle and leg exercises.
- Knee range-of-motion exercises.
- Progressive strengthening.
The goal is safe movement, not forcing the knee through severe pain.
Why Is Early Walking Important?
- Helps reduce prolonged immobility.
- Supports circulation.
- Helps reduce blood-clot risk.
- Reduces muscle deconditioning.
- Supports recovery of walking function.
- Builds confidence with the new knee.
Early movement should always be supervised initially and adjusted to the patient’s medical condition.
How Is Pain Controlled After Knee Replacement?
Modern knee replacement programs usually use multimodal pain management rather than relying on a single strong pain medicine.
- Paracetamol or acetaminophen when appropriate.
- Anti-inflammatory medicines when medically suitable.
- Regional nerve blocks in selected patients.
- Local anesthetic around the surgical area.
- Short-term opioid medication when necessary.
- Ice and elevation.
- Early but controlled movement.
Pain management is individualized, especially in patients with kidney disease, stomach ulcers, cardiovascular disease, sleep apnea or other conditions that affect medication choices.
How Long Do You Stay in the Hospital After Knee Replacement?
Hospital stay varies according to the surgical approach, patient health, mobility, pain control and local hospital protocols.
- Some appropriately selected patients may be discharged on the same day.
- Many uncomplicated patients stay overnight or for a short inpatient stay.
- Some patients require one to several additional days.
- Patients with significant medical problems or complications may require longer hospitalization.
A commonly quoted hospital stay for uncomplicated knee replacement is around 1 to 3 days, but modern enhanced-recovery pathways can allow earlier discharge for appropriately selected patients.
When Can I Be Discharged From the Hospital?
Discharge is based on clinical readiness rather than simply counting postoperative days.
- Vital signs are stable.
- Pain is reasonably controlled with an appropriate medication plan.
- The wound is satisfactory.
- You can safely get in and out of bed.
- You can walk safely with the recommended aid.
- You can use the bathroom safely.
- You can eat and drink adequately.
- There is no immediate medical concern requiring hospitalization.
- A safe home-care and follow-up plan is available.
Do I Need a Walker After Knee Replacement?
Many patients initially use a walker or crutches because the knee is painful, swollen and the muscles are temporarily weak.
The walking aid is gradually reduced as strength, balance and confidence improve. The exact timeline varies from patient to patient.
What Happens During the First Week?
- Pain and swelling are expected.
- Walking is gradually increased.
- Physiotherapy focuses on safe movement and knee range of motion.
- The wound is monitored.
- Blood-clot prevention is continued according to the prescribed plan.
- You gradually become more independent with daily activities.
The knee may feel stiff and uncomfortable during the first several days. Improvement is usually gradual rather than immediate.
Physiotherapy After Knee Replacement
Physiotherapy is one of the most important components of knee replacement recovery. The purpose is to restore movement, strength, balance and functional independence.
- Knee range-of-motion exercises.
- Quadriceps strengthening.
- Straight-leg raises when appropriate.
- Walking practice.
- Stair training.
- Balance exercises.
- Progressive strengthening.
- Functional activities.
Why Knee Movement Matters After Surgery
A knee that remains very stiff after surgery can be difficult to rehabilitate. The rehabilitation program therefore aims to restore movement while controlling pain and swelling.
The exact exercise program should be individualized. Forcing the knee aggressively can increase pain and swelling and is not a substitute for structured rehabilitation.
How Much Pain Is Normal After Knee Replacement?
Pain, soreness and swelling are expected after knee replacement. The important feature is that symptoms should gradually become more manageable over time.
Severe or rapidly worsening pain, especially when accompanied by fever, wound drainage, increasing redness or calf swelling, should be medically assessed.
How Long Does Full Recovery Take?
Recovery is progressive. Many patients become independently mobile relatively early, but full recovery of strength, endurance and confidence can take several months.
The timeline varies with age, fitness, muscle strength, preoperative mobility, medical conditions, surgical complexity and adherence to rehabilitation.
- First days: pain control and safe walking.
- First few weeks: progressive mobility and physiotherapy.
- Around 4 to 6 weeks: increasing independence for many patients.
- Around 6 to 12 weeks: substantial functional improvement is common.
- Several months: continued improvement in strength, endurance and confidence.
When Can I Drive After Knee Replacement?
Driving should wait until you can safely control the vehicle, perform an emergency stop and are no longer impaired by sedating pain medicines.
The timing varies according to whether the surgery was on the right or left knee, whether the vehicle is automatic or manual and individual recovery. Follow your surgeon’s advice and check applicable insurance requirements.
When Can I Return to Work?
Return to work depends heavily on the type of work.
- Desk-based work may be possible earlier.
- Jobs requiring prolonged standing may require additional recovery.
- Manual labor usually requires a longer rehabilitation period.
- Jobs involving climbing, kneeling or heavy lifting may require additional restrictions.
Your surgeon and rehabilitation team can help determine when you are ready for your specific occupation.
When Can I Climb Stairs?
Stair training is commonly included before discharge. Patients may initially use a handrail and walking aid and should follow the technique taught by the physiotherapist.
Being able to climb stairs safely does not mean the knee is fully recovered.
When Can I Exercise After Knee Replacement?
Low-impact activities are generally favored after knee replacement because they provide cardiovascular and muscular benefits without excessive joint impact.
- Walking.
- Stationary cycling.
- Swimming after the wound has fully healed.
- Low-impact aerobic exercise.
- Strength training under guidance.
- Flexibility and balance exercises.
High-impact activities such as repeated running and jumping may not be recommended depending on the patient, implant and surgeon’s advice.
Can I Kneel After Knee Replacement?
Kneeling is not medically necessary for most daily activities, and some patients find it uncomfortable after knee replacement. If kneeling is important for your work or religious practices, discuss this with your surgeon before surgery.
The ability to kneel varies from person to person.
What Are the Risks of Knee Replacement Surgery?
Knee replacement is a commonly performed operation, but like every major surgery it carries potential risks.
- Infection.
- Blood clot in the leg or lungs.
- Bleeding.
- Wound-healing problems.
- Persistent pain.
- Knee stiffness.
- Instability.
- Nerve or blood-vessel injury.
- Fracture around the implant.
- Implant wear or loosening.
- Dislocation or instability in selected circumstances.
- Need for revision surgery.
Infection After Knee Replacement
Infection around an artificial knee is an important complication because an infection involving the implant may require prolonged antibiotics and sometimes additional surgery.
Tell your medical team about active infections before elective surgery. After surgery, increasing redness, wound drainage, fever or worsening pain should be assessed promptly.
Blood Clots After Knee Replacement
Knee replacement increases the risk of venous blood clots because surgery and reduced mobility affect blood flow and clotting.
- Early mobilization.
- Leg and ankle exercises.
- Compression devices or stockings when prescribed.
- Anticoagulant or antiplatelet medication when prescribed.
- Following the postoperative mobility plan.
The exact blood-thinning medication and duration depend on the patient’s individual clotting and bleeding risks.
Warning Signs of a Blood Clot
- New or increasing swelling in one leg.
- Calf pain or tenderness.
- Warmth or discoloration of the leg.
- Sudden shortness of breath.
- Chest pain.
- Coughing blood.
Sudden breathing difficulty or chest pain after surgery requires urgent medical evaluation because a blood clot can travel to the lungs.
Knee Stiffness After Replacement
Some stiffness is common during early recovery. Persistent significant loss of movement may require additional assessment and a more intensive rehabilitation plan.
In selected cases, a procedure called manipulation under anesthesia may be considered when substantial stiffness persists despite appropriate rehabilitation.
Persistent Pain After Knee Replacement
Most patients experience meaningful pain relief, but some continue to have pain after surgery. Persistent pain should be investigated rather than simply accepted as normal.
Possible causes include infection, stiffness, instability, implant loosening, nerve-related pain, referred pain from another part of the body or other musculoskeletal problems.
How Long Does a Knee Replacement Last?
Modern knee replacements are designed to provide durable long-term function. Many knee replacements last around 20 years or longer, although implant survival varies between patients and depends on factors such as age, activity, implant type, weight, alignment and complications.
A younger patient may eventually require revision surgery because the implant has been in place for many years, but revision is not inevitable.
What Can Cause a Knee Replacement to Fail?
- Infection.
- Implant loosening.
- Polyethylene wear.
- Instability.
- Fracture around the implant.
- Significant stiffness.
- Persistent unexplained pain.
- Trauma.
Can a Knee Replacement Be Replaced Again?
Yes. Revision knee replacement is possible when a previous implant fails or develops a significant complication.
Revision surgery is generally more complex than primary knee replacement and may involve specialized implants, bone reconstruction or treatment of infection.
What Should I Eat Before Knee Replacement?
A balanced diet before surgery can support general health and recovery.
- Adequate protein.
- Vegetables and fruits.
- Whole grains and other nutritious carbohydrates.
- Adequate fluids unless medically restricted.
- Iron-rich foods when appropriate.
- Calcium- and vitamin-D-containing foods as appropriate.
If you have diabetes, kidney disease, obesity, anemia or another condition requiring dietary management, follow your healthcare professional’s individualized advice.
What Should I Eat After Knee Replacement?
After surgery, adequate protein, fluids and nutrient-rich foods can support recovery. Fibre is also useful for preventing constipation, particularly when pain medicines reduce bowel movement.
- Eggs.
- Fish.
- Chicken.
- Lean meat.
- Milk and yogurt when tolerated.
- Dal and lentils.
- Beans and chickpeas.
- Vegetables.
- Fruits.
- Whole grains.
- Adequate fluids.
What Should I Prepare at Home Before Knee Replacement?
- Arrange transportation home.
- Arrange help during the early recovery period.
- Prepare easy-to-reach frequently used items.
- Prepare meals in advance.
- Remove loose rugs and trip hazards.
- Arrange a safe sleeping and bathroom setup.
- Consider a raised toilet seat or other equipment if recommended.
- Keep prescribed medicines organized.
- Arrange physiotherapy according to your discharge plan.
What Should Family Members Know?
Family support can make early recovery easier. The patient may be mobile but still unable to perform heavier household tasks.
- Help with transportation.
- Assist with meals and shopping.
- Help with household tasks.
- Support safe walking when needed.
- Encourage prescribed exercises without forcing the patient.
- Watch for warning signs.
- Help ensure medications are taken correctly.
Knee Replacement in Older Adults
Age alone should not automatically prevent a patient from having knee replacement. Overall health, independence, frailty, heart and lung function, cognitive status and the ability to participate in rehabilitation are more important considerations.
Older adults may require additional planning for fall prevention, home support, medication management and rehabilitation.
Knee Replacement in Younger Patients
Younger patients may also require knee replacement when arthritis or joint damage causes severe symptoms and other treatments are no longer effective.
Because the implant may need to function for many decades, implant longevity, activity expectations and the possibility of future revision should be discussed carefully before surgery.
What Questions Should I Ask My Orthopedic Surgeon?
- Why do I need knee replacement now?
- Is total or partial replacement better for my knee?
- What happens if I postpone surgery?
- What type of implant do you recommend and why?
- Will you use cemented or cementless fixation?
- Will my kneecap be resurfaced?
- What type of anesthesia do you recommend?
- Will I need a nerve block?
- Will I need ICU monitoring?
- How long do you expect me to stay in hospital?
- When will I start walking?
- What physiotherapy will I need?
- What are my individual risks of infection and blood clots?
- When can I drive?
- When can I return to work?
- When can I exercise?
- What symptoms should make me contact the hospital?
The Complete Knee Replacement Journey
- Step 1: Confirm that the symptoms and arthritis justify surgery.
- Step 2: Discuss non-surgical alternatives and expected benefits.
- Step 3: Complete medical and anesthesia assessment.
- Step 4: Optimize conditions such as diabetes, anemia and blood pressure.
- Step 5: Prepare the home and rehabilitation plan.
- Step 6: Attend the hospital for surgery.
- Step 7: Receive spinal/regional or general anesthesia as planned.
- Step 8: Damaged knee surfaces are prepared and implants positioned.
- Step 9: Recover in the postoperative area and receive pain control.
- Step 10: Begin safe walking and physiotherapy.
- Step 11: Meet discharge criteria and return home when clinically safe.
- Step 12: Continue physiotherapy and gradually increase activity.
- Step 13: Attend postoperative follow-up and continue long-term joint care.
When Should You Contact Your Doctor After Knee Replacement?
- Increasing rather than improving knee pain.
- Fever or chills.
- Increasing redness or warmth around the wound.
- Pus or significant drainage from the wound.
- Increasing swelling of the knee or leg.
- New calf pain or swelling.
- Difficulty moving the leg that is suddenly worse.
- A new wound opening.
- Persistent severe pain despite prescribed medication.
When Is Emergency Care Needed?
Seek urgent medical attention for sudden difficulty breathing, significant chest pain, fainting or other symptoms suggesting a serious complication.
A blood clot can occasionally travel to the lungs and cause a pulmonary embolism, which requires immediate treatment.
What Makes a Successful Knee Replacement?
A successful knee replacement is not determined by the implant alone. Good outcomes depend on appropriate patient selection, careful surgical technique, infection prevention, effective pain control, early safe mobilization and consistent rehabilitation.
- Correct diagnosis.
- Appropriate timing of surgery.
- Good medical preparation.
- Appropriate implant selection.
- Accurate surgical technique.
- Effective pain management.
- Early safe mobilization.
- Patient participation in rehabilitation.
- Good long-term health and activity habits.
A Senior Surgeon’s Perspective
The decision to perform a knee replacement should never be based on an X-ray alone. I would consider the patient’s pain, walking ability, sleep, daily function, deformity, range of motion, medical fitness and expectations before recommending surgery.
The best knee replacement is not necessarily the newest or most expensive technology. The right operation is the one that matches the patient’s disease pattern, anatomy, health, functional requirements and realistic expectations.
Patients should also understand that knee replacement is designed primarily to relieve pain and improve function. It is not intended to reproduce the exact sensation or movement of a completely normal young knee.
How MedGoPlus Can Help
Preparing for knee replacement can involve many questions about the operation, anesthesia, hospital stay, rehabilitation, nutrition and recovery.
MedGoPlus can help patients connect with qualified healthcare professionals for consultations, surgical guidance and postoperative follow-up through available consultation services.
Medical Disclaimer
This article is intended for general health education and does not replace an examination or individualized advice from an orthopedic surgeon, anesthetist, physiotherapist or other healthcare professional. Knee replacement decisions, anesthesia plans, medications, discharge timing and rehabilitation vary between patients.
Take Control of Your Health with MedGoPlus
Book doctor consultations, manage your health needs, and access convenient healthcare services anytime, anywhere with the MedGoPlus App.
Scan to download
Download the MedGoPlus App

